


Posterior tongue tie is a deeper, submucosal tethering under the tongue that restricts movement without the visible cord anterior ties show. If your baby has feeding problems, the right first step is a functional assessment and lactation support, not an immediate procedure. Surgery gets considered only when restricted tongue movement clearly explains ongoing feeding difficulty. Start by watching feeds closely and calling a lactation consultant or pediatrician.
TL;DR:
- Most feeding issues attributed to posterior tongue tie often improve with lactation support and positioning changes, reducing unnecessary surgery in many cases.
- Diagnosis relies on observing feeding performance and tongue mobility rather than appearance alone, with functional assessments outweighing visual checks.
- Surgery options, such as frenotomy and frenuloplasty, carry risks and should only be considered after documented, persistent feeding problems despite conservative care.
- Research shows limited evidence of long-term benefits from frenotomy, with short-term pain relief being the main supported outcome; many infants get better without surgery.
- A coordinated, functional assessment approach involving lactation support and careful follow-up is essential before proceeding with any surgical intervention.
Table of Contents
- Signs of Tongue Tie: What to Watch During Feeding
- How Do Doctors Diagnose Posterior Tongue Tie?
- Treatment Options for Posterior Tongue Tie
- What Happens After a Frenotomy: Recovery and Follow-Up
- What the Research Really Shows About Posterior Tongue Tie
- A Quick Decision Checklist Before Pursuing a Release
- One Clinic’s Approach to Coordinated Tongue Tie Care
- Considering an Evaluation for Your Baby?
- Sources
Signs of Tongue Tie: What to Watch During Feeding
Posterior tongue tie hides in plain sight. Because the tissue sits farther back and under a layer of mucosa, a quick peek in the mouth often misses it entirely, which is exactly why so many diagnoses lean on how a baby feeds instead of how the mouth looks.
Watch for these patterns during breastfeeding:
- A latch that slips, clicks, or won’t stay put
- Nipple pain or visible damage that doesn’t improve with repositioning
- Feeds that take a long time or happen frequently without satisfying the baby
- Weak or absent audible swallowing during a feed
- Slow weight gain despite frequent nursing
Bottle-fed babies show it differently. They cough, leak milk from the corners of the mouth, or tire halfway through a bottle. One U.S. lactation program found that 63% of babies referred for tongue-tie surgery did not actually need the procedure once their feeding was properly assessed and supported. That number alone should make any parent pause before assuming surgery is the answer.
Claims about tongue tie causing later speech delays or dental crowding circulate widely, but the evidence backing those long-term effects is much thinner than the feeding evidence. Track feed length, diaper output, and whether you hear rhythmic swallowing. Bring notes to your appointment. Specifics help a clinician far more than “feeding seems hard.”
How Do Doctors Diagnose Posterior Tongue Tie?
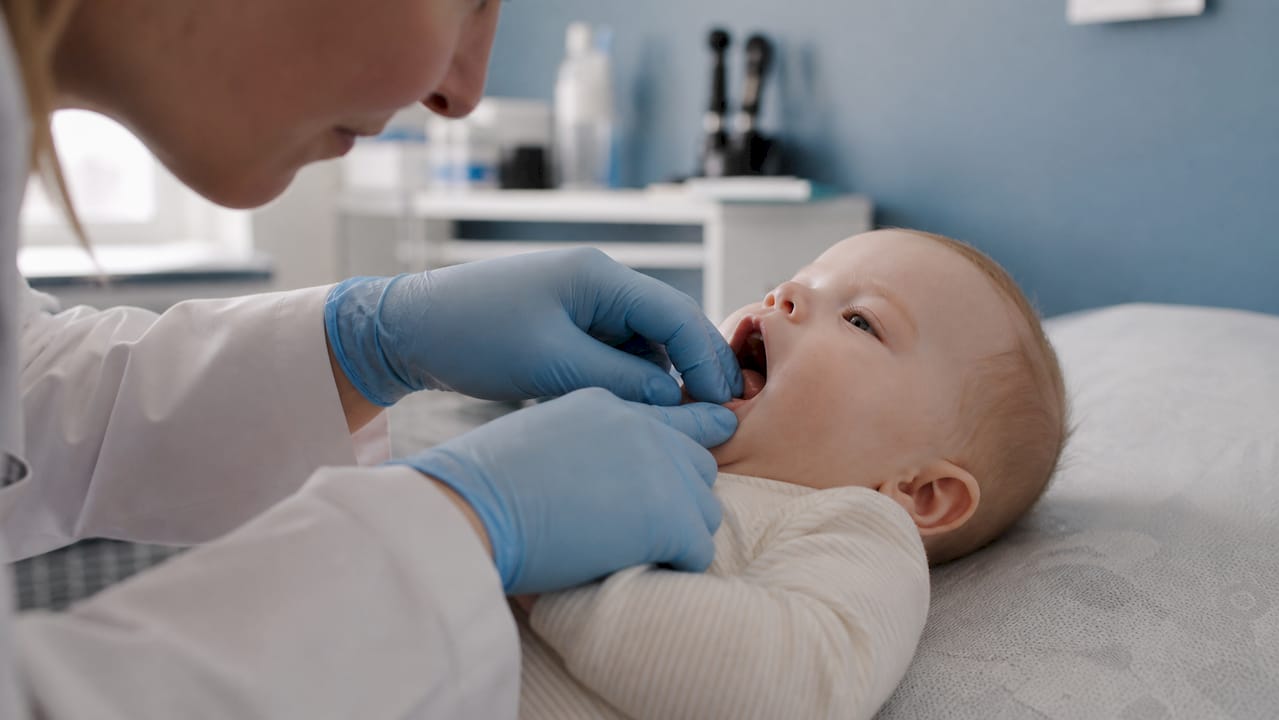
Appearance alone misleads. A frenulum can look unremarkable while still limiting tongue lift, and a visible tie can exist without ever causing a feeding problem. That mismatch is why functional assessment carries more diagnostic weight than a visual check, and why a growing number of clinics build their evaluation process around watching a baby actually feed.
A thorough assessment typically covers:
- Tongue lift and extension. Can the tongue rise toward the roof of the mouth or reach past the lower lip?
- Lateral movement. Can the baby move the tongue side to side, which matters for both breast and bottle feeding?
- Suction and flange. Does the baby maintain a seal, and do the lips flange outward normally instead of curling in?
- Observed feeding. A clinician or lactation consultant watches an actual feed rather than relying on a parent’s description.
- Pre and post feed weight checks. Weighing the baby before and after nursing estimates real milk transfer.
Pediatricians, lactation consultants, pediatric dentists, ENTs, and speech-language pathologists all play a role depending on the case. A referral for surgical evaluation usually follows only after documented feeding problems persist despite lactation support, not from a single office visit where someone glances under the tongue.
Treatment Options for Posterior Tongue Tie
Most cases start with conservative care, not a scalpel or laser. Expert lactation support, covering positioning changes, latch coaching, and sometimes temporary pumping or supplementation, resolves a meaningful share of feeding struggles that get blamed on tongue tie. Breastfeeding problems are usually multifactorial, and treating the whole picture often solves what looked like a tongue problem.
When conservative measures don’t fix a documented functional restriction, two surgical paths exist:
- Frenotomy. A quick, often anesthesia-free release performed in an office setting for many infants, using scissors or a laser.
- Frenuloplasty. Reserved for thicker or more complex tethering that needs an operating room, deeper incision, and stitches.
Both carry real risks worth naming plainly. Bleeding, scarring, and, rarely, injury to a nearby salivary duct can occur. In the FROSTTIE randomized trial, minor complications occurred in a small number of infants who underwent frenotomy. That’s a small number, but it’s not zero, and any clinician recommending the procedure should walk you through it before you consent.
Pro Tip: Ask whether myofunctional therapy is part of the plan before you agree to a release. A frenotomy changes the anatomy, but it doesn’t automatically retrain how the tongue moves. Babies and toddlers often need guided exercises afterward to actually use the new range of motion.
What Happens After a Frenotomy: Recovery and Follow-Up
Recovery from an office-based frenotomy is typically fast. Many babies nurse within minutes of the release, right in the exam room, which lets the clinician and a lactation consultant watch the latch change in real time. Frenuloplasty performed under anesthesia in an operating room involves a longer recovery window and closer monitoring afterward.

A release alone rarely finishes the job. Continued lactation support in the days after the procedure catches early problems, and guided tongue exercises improve the odds of a lasting benefit rather than a quick fix that fades.
Call your pediatrician promptly if you notice:
- Bleeding that doesn’t stop within a few minutes
- Signs of infection, including fever or unusual discharge
- Feeding that gets worse instead of better over the following week
- Refusal to feed at all after the procedure
What the Research Really Shows About Posterior Tongue Tie
The honest answer is: less than you’d expect from how often frenotomy gets recommended. The FROSTTIE trial found no clear difference in breastfeeding continuation at three months between infants who got an immediate frenotomy plus support versus support alone, though some studies note short-term nipple pain relief. Trials in this area tend to be small and underpowered, which limits how confidently anyone can generalize the results.
A separate review of posterior tongue tie and breastfeeding found a plausible short-term role in feeding difficulty, but little solid evidence connecting it to speech or later feeding milestones. Meanwhile, pediatric guidance warns that fewer than half of infants with a visible frenulum actually have nursing problems requiring surgery.
Put those two facts together and the picture gets clearer:
- Short-term pain relief for the parent is a real, if modest, finding in some studies
- Long-term breastfeeding or developmental benefit is not consistently demonstrated
- A large share of referred infants improve with support alone, no surgery needed
A Quick Decision Checklist Before Pursuing a Release
Consider evaluation or release when you can check off more than one of these:
- Documented poor milk transfer or slow weight gain, not just a hunch
- Nipple trauma or pain that persists despite proper lactation support
- Observed tongue restriction that a clinician directly connects to the feeding problem
- Conservative measures tried for a reasonable stretch without improvement
Ask any provider recommending a frenotomy: what specific tests confirmed the restriction, what improvement should we expect, what are the risks, and what does follow-up care look like?
Pro Tip: Seek same-day medical review if you notice dehydration signs (very few wet diapers, sunken fontanelle) or if weight loss exceeds what your pediatrician flags as normal for age. Those are not “wait and see” situations.
One Clinic’s Approach to Coordinated Tongue Tie Care
Bay Area Dental, Airway & Sleep in Fremont, California, built its pathway around exactly this functional model: assessment first, imaging and laser-assisted release only when indicated, and myofunctional therapy alongside lactation follow-up afterward. The practice pairs 3D imaging with minimally invasive laser tools when a release is genuinely warranted, rather than defaulting to surgery.
This is one example of what coordinated care can look like, not the only correct model. Whatever clinician you choose, insist on the same functional assessment and follow-up plan before agreeing to any procedure.
— Admin
Considering an Evaluation for Your Baby?
If you’ve read this far because something about your baby’s feeding still feels off, an in-person functional assessment beats another night of googling symptoms. Bay Area Dental, Airway & Sleep offers coordinated evaluations that combine lactation input, tongue mobility testing, and minimally invasive laser release when the assessment actually supports it, so you’re not choosing between “do nothing” and “surgery now” without anything in between.

This isn’t the only path to take after reading this guide, but if you’re in the Bay Area and want a clinic built around functional diagnosis rather than a quick glance under the tongue, schedule a tongue tie evaluation and bring your feeding notes with you.
Sources
- Ankyloglossia (Tongue “Tie”) – StatPearls – NCBI Bookshelf
- Ankyloglossia (Tongue “Tie”) – URMC Rochester
- Review: breastfeeding support and tongue tie – PMC
- Healthychildren
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.